
Consulting has no catchment. Staffing still does.
Remote consulting removes the travel constraint, then replaces it with two others: which registration a clinician holds, and whether anyone is free at the hours your demand actually arrives. Both are staffing problems, and both are ours.
Three things, and none of them touch your consulting software.
Each links deeper rather than explaining itself here.
Start from the clinicians you already use
Your existing consultants become a standing list with registration and indemnity attached and dated. Filling a session starts with someone who already knows your platform rather than with a stranger and a credentialing pack.
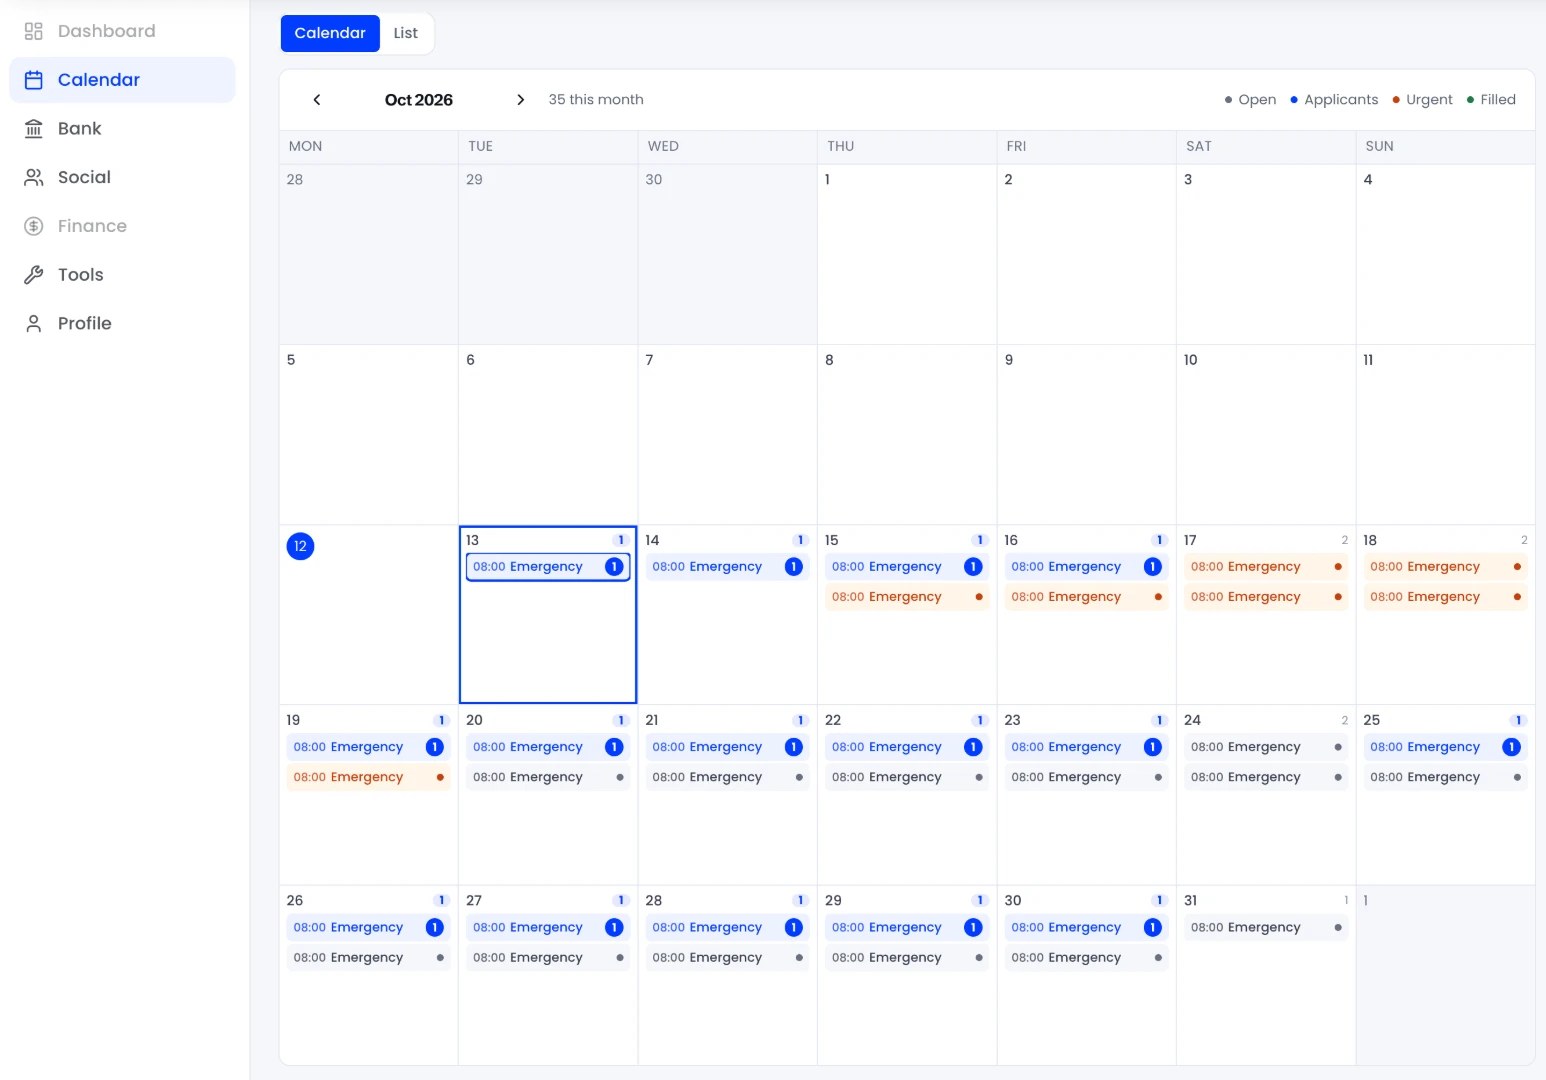
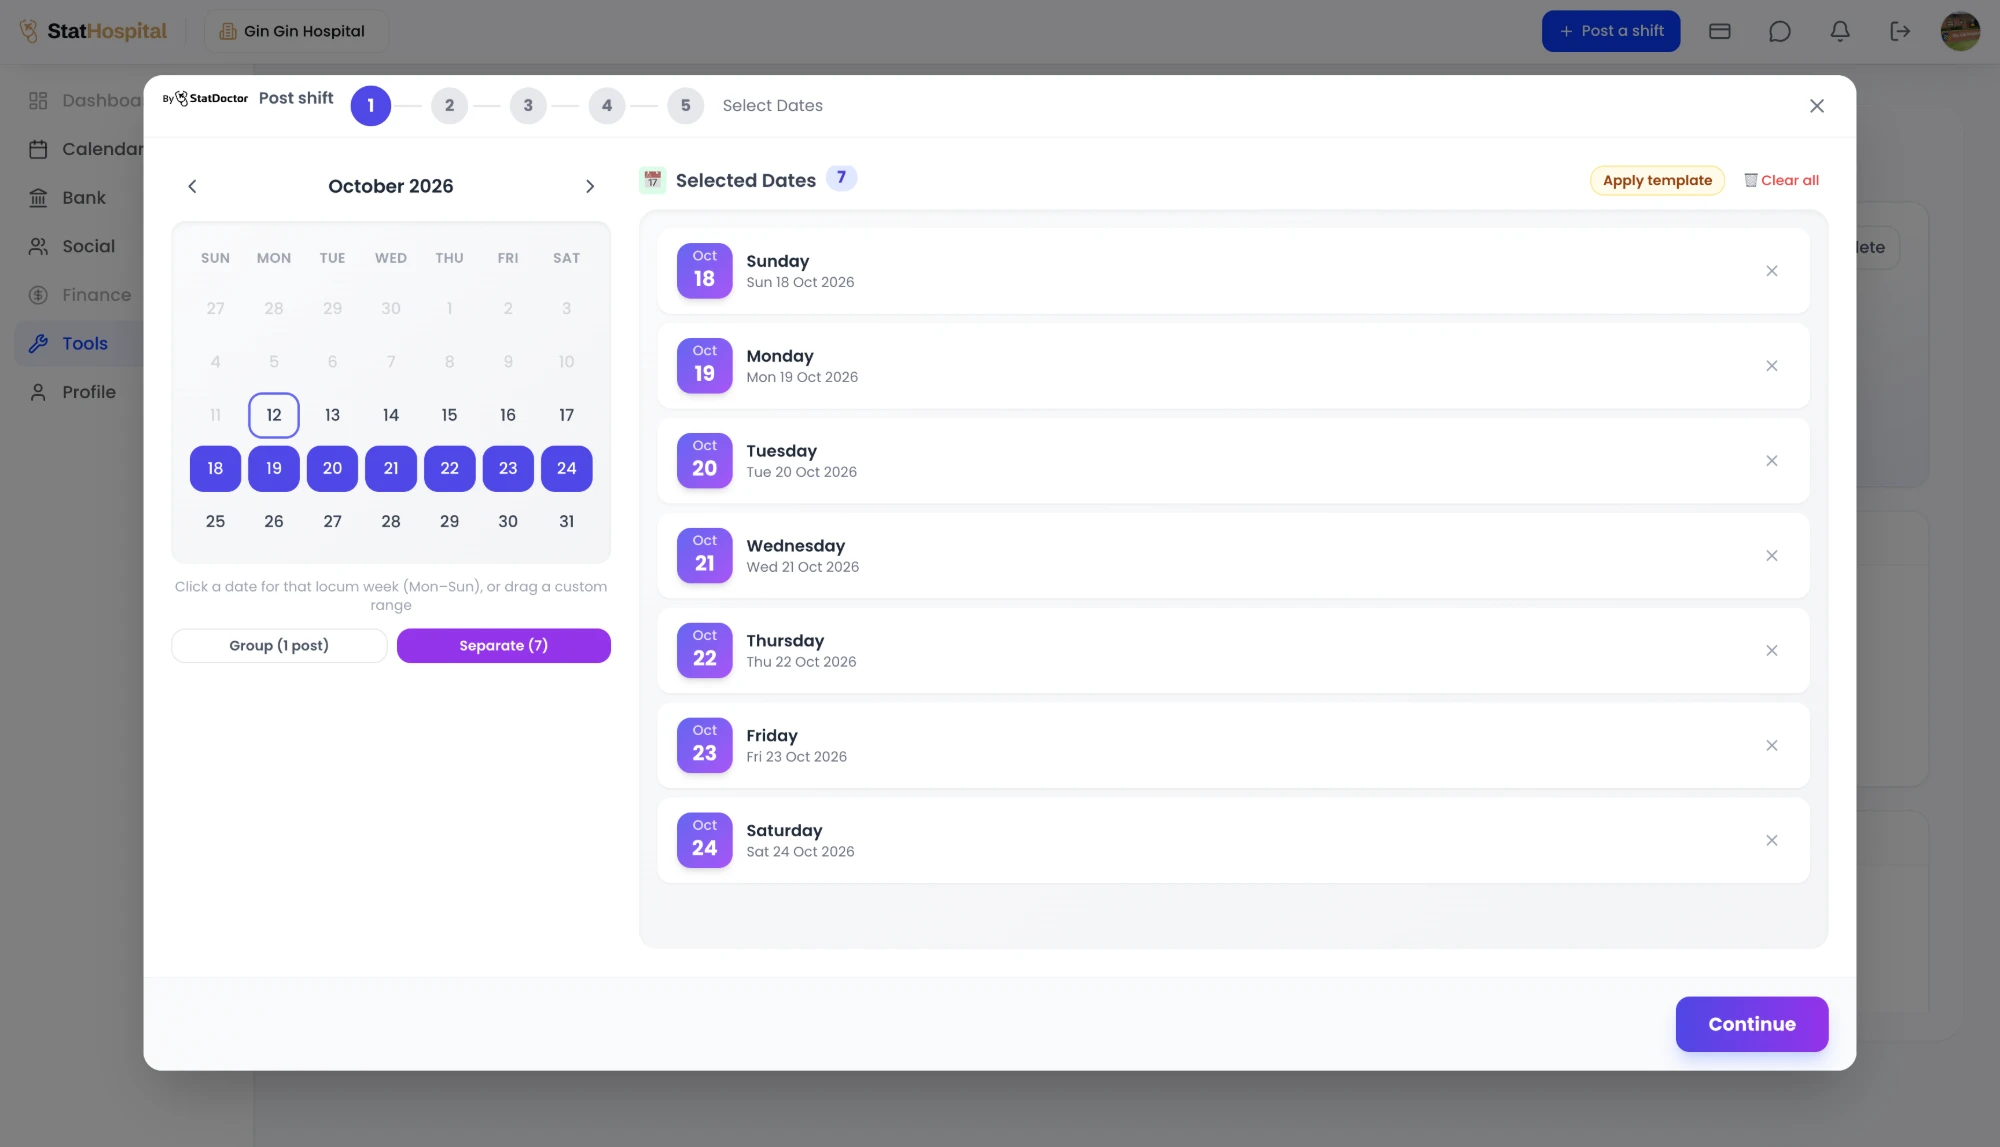
Post for when demand actually lands
Evenings, weekends and public holidays, which is exactly when a conventional roster is thinnest. The point of a national pool is that someone, somewhere, wants the Sunday evening you cannot fill locally.
Evidence that re-checks itself
Registration type, endorsements and conditions held per clinician and re-checked as they expire. Remote consulting makes this more important rather than less: there is no front desk that would notice a lapsed certificate.
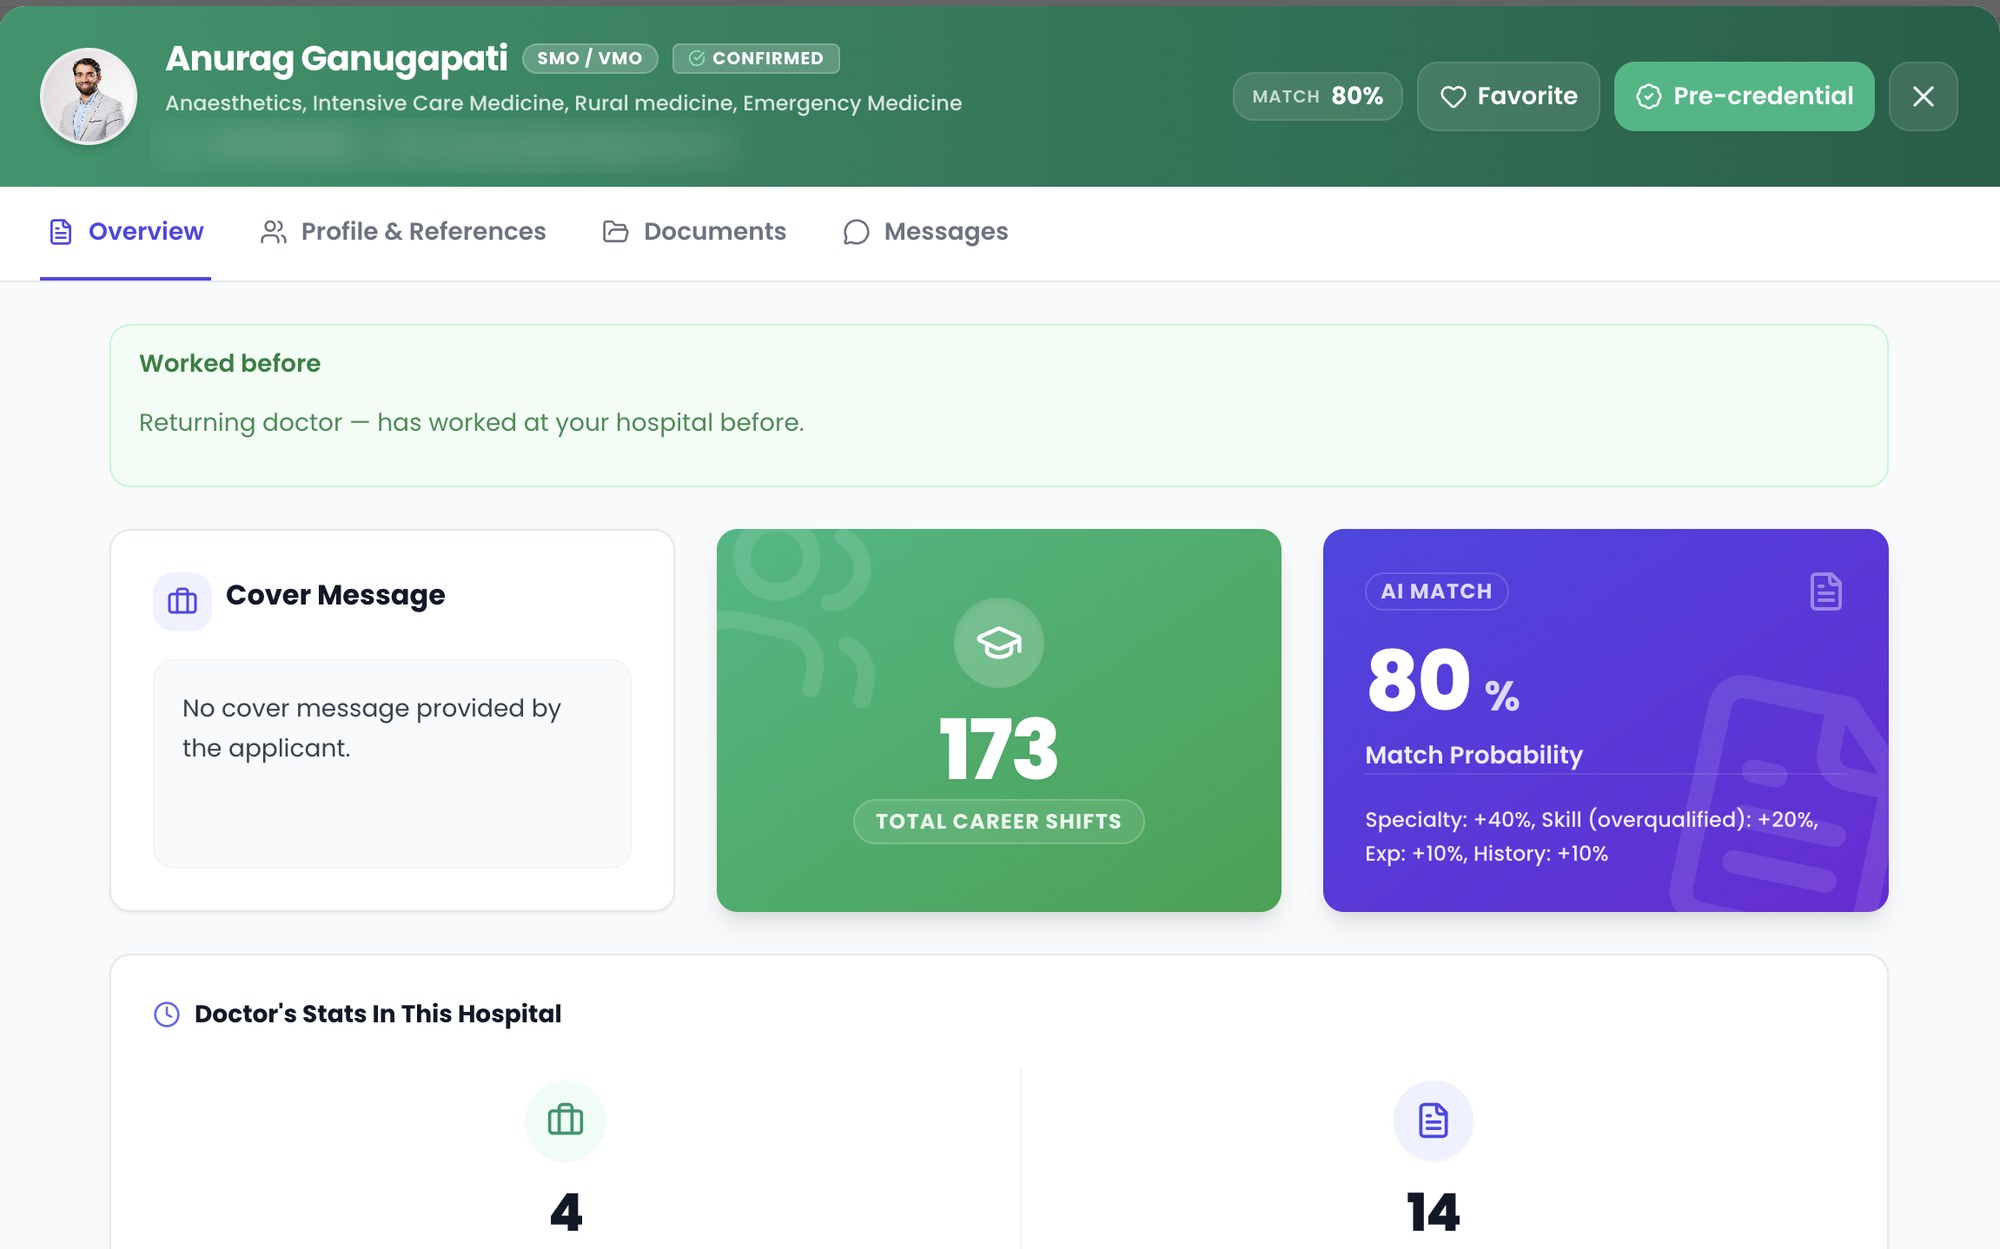
What you are reaching into.
What it looks like when it works.
- 1
A Sunday evening block opens
The hours nobody local wants. The session goes to clinicians who have told the platform those are exactly the hours they do want.
- 2
Registration is already verified
Type, endorsements and conditions held per clinician and current, so you can see what someone is registered to do before you roster them.
- 3
They consult on your platform
Your software, your protocols, your clinical governance. We are the staffing layer underneath, not a video vendor.
- 4
And they stay on your bank
The next Sunday starts from someone who already knows your systems rather than from a search.
Not a video vendor, not a scope assessor.
You keep your consulting software. You keep the decision about which clinician is appropriate for which consultation, and about what your service should be offering. We hold the people and the evidence.
Telehealth staffing, answered.
How do telehealth providers staff consultations across Australia?
By holding a bank of clinicians rather than recruiting per session. Remote consulting removes geography from the problem, so the pool is national, but it adds registration and availability constraints instead. A standing list of clinicians who already know your platform and protocols is what makes an evening session fillable at short notice.
Does AHPRA registration work across state borders for telehealth?
AHPRA registration is national, so a doctor registered in one state is registered everywhere. What is specific to the individual is their registration type, any endorsements and any conditions, and those determine the work they can do. We hold that evidence against every clinician on your bank and re-check it as it expires. Whether a given clinician is appropriate for a given consultation is your clinical governance decision.
Why is after-hours telehealth demand hard to staff?
Because demand concentrates in evenings and weekends, which is exactly when a conventional roster is thinnest. This is the part telehealth providers most often get wrong: they staff to average demand and then discover the average hides the peak. A bank widens the pool you can reach at those hours, though whether it fills still depends on how many clinicians are in it and what the work pays.
Do you supply telehealth software?
No. You keep whatever consulting platform you already use. StatDoctor is the staffing and credentialing layer underneath it: finding clinicians, holding their documents and keeping the evidence current. We are not a video vendor and have no intention of becoming one.
Can we use clinicians we already work with?
Yes, and most providers start exactly there. A bank usually begins as the clinicians you already trust. StatHospital gives that list somewhere to live, with current registration and indemnity attached, instead of a spreadsheet and somebody's inbox.
How is credentialing handled when nobody meets in person?
The same way it should be handled anywhere: registration, indemnity and identity verified on joining and re-checked as they approach expiry. Remote consulting makes this more important rather than less, because there is no front desk that would notice a lapsed certificate.
StatDoctor is free for clinicians and takes no margin on the rate. Providers pay for StatHospital; pricing follows the size of your bank and which parts of the platform you use. No charge for an initial conversation and no obligation after one.
Which sessions go unfilled?
Start with the hours you cannot cover and what you currently do about them. We will tell you plainly whether this is a problem we can help with.