
Two staffing problems wearing one name.
Reporting can be covered from anywhere by anyone credentialed and free at the time. An interventional list cannot. Treating those as the same roster problem is why one of them keeps falling over, and it is the one worth building a bank for.
Three things, starting with the split most practices skip.
Each links deeper rather than explaining itself here.
A national pool, once availability is the constraint
Reporting does not need the clinician on site, so geography stops mattering and availability starts. Posting sessions to a standing bank is what turns a national pool into a session that actually fills.
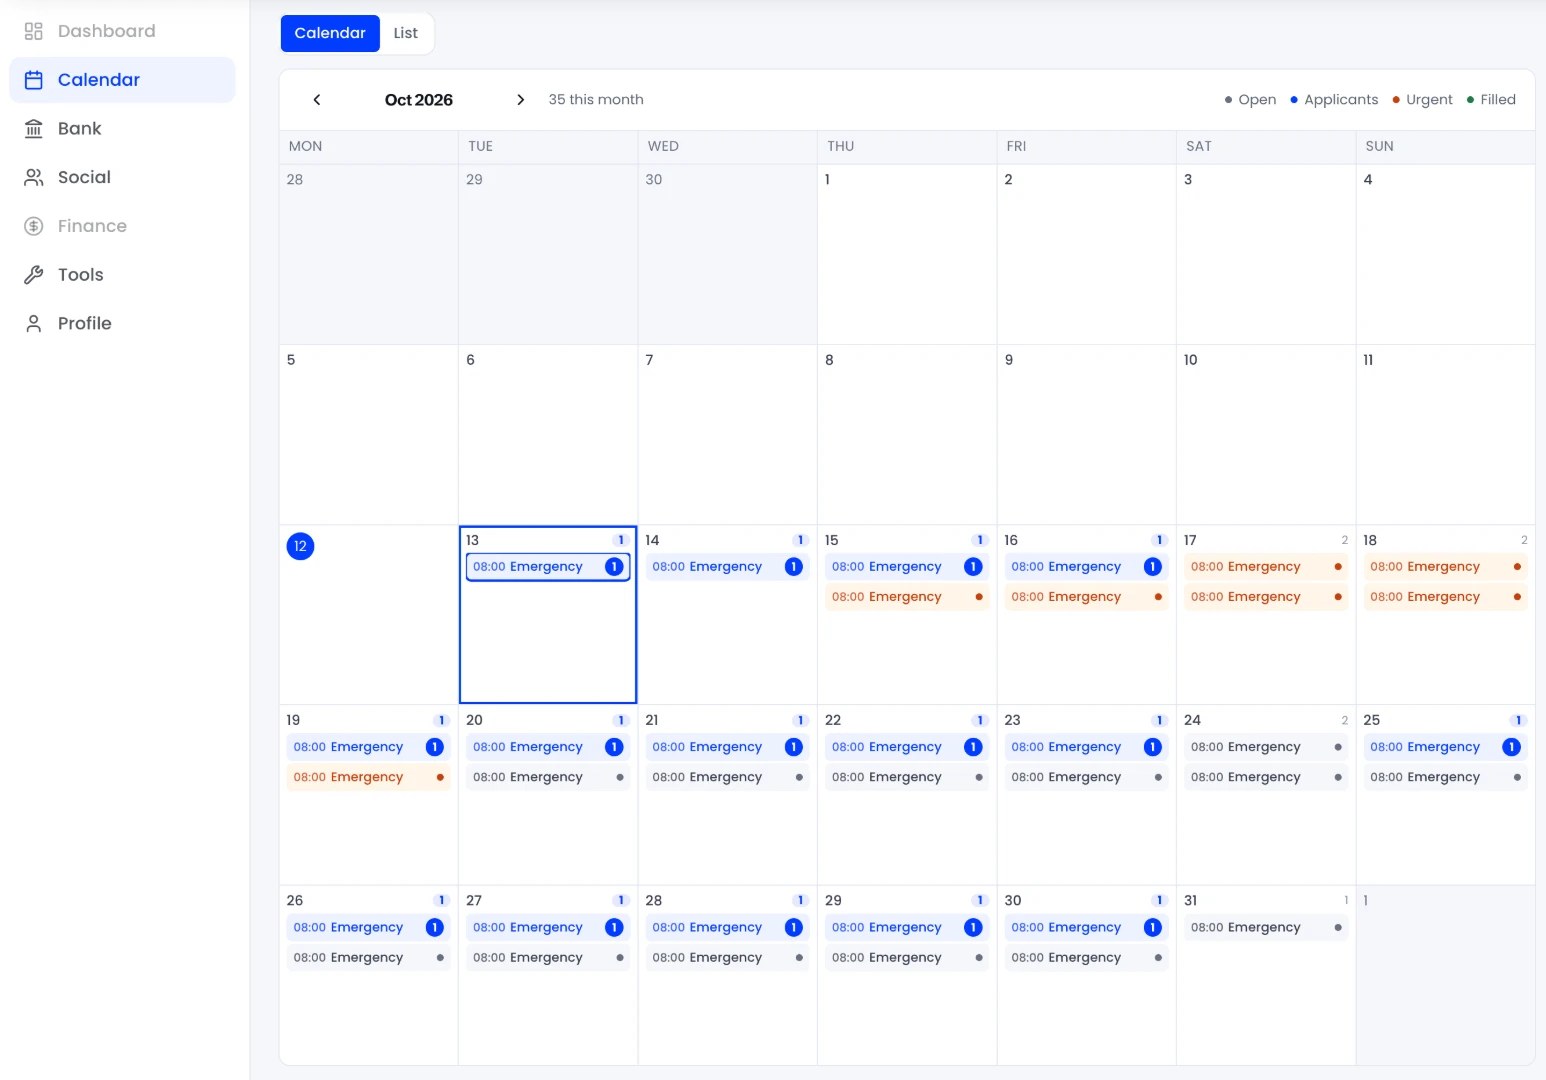
The lists that need a body in the room
Interventional and contrast work bring proximity back, which makes these the hardest sessions to fill at short notice. Treating them as the same problem as reporting is why one of the two keeps quietly failing.
Re-checked, not just collected
Registration and indemnity held with expiry dates and re-checked as they approach. For a practice without a medical administration department, that is the difference between compliant and lucky.
What you are reaching into.
What it looks like when it works.
- 1
Split the two problems
Reporting and on-site posted as different things, because they draw on different pools and fail for different reasons.
- 2
Reporting goes wide
Anyone appropriately registered and free at the time, anywhere in the country. Notice and rate do the work that geography used to.
- 3
On-site goes to the bank first
The narrowest pool, reached through people who have already worked your rooms and whose evidence is current.
- 4
Nobody is named without permission
Your operator name appears nowhere public unless you give it in writing. That is the default, and nothing about the service depends on changing it.
We will not name you, by default.
The operator names behind the radiology sites on our network are not ours to publish, so we do not: not here, and on the coverage map only as a suburb behind a generic mark. If you would rather be named, that is a permission you give us in writing. Most groups do not, and nothing about the service depends on it.
Radiology staffing, answered.
How do radiology practices cover reporting sessions?
Reporting does not require the clinician on site, so the pool is national rather than local, but it still requires someone credentialed, available for that session, and comfortable with your modality and PACS. A standing bank of radiologists who have reported for you before is what turns a national pool into a session that actually fills.
How is on-site radiology cover different from reporting cover?
Proximity comes back. Interventional lists, contrast work and anything needing a clinician physically present cannot be solved by widening the map, which makes these the hardest sessions to fill at short notice and the ones a standing bank helps with most. Treating both as one roster problem is why one of them keeps failing.
Which radiology groups do you work with?
We do not publish that. StatDoctor is not licensed to use the operator names behind the radiology sites on its network, so they appear nowhere public: not on this page, and on our coverage map only as a suburb behind a generic mark. If being named matters to you, that is a permission you give in writing, not one we assume.
Do you supply radiologists, or software?
Neither alone. StatHospital is where your bank lives and where credentialing evidence is held and re-checked. The clinicians come from your existing relationships plus the StatDoctor network. We do not employ radiologists and we are not a PACS or RIS vendor.
Can reporting be covered from another state?
Usually, and that is the practical advantage of reporting work. AHPRA registration is national; what is specific to the individual is their registration type, endorsements and any conditions. We hold that evidence per clinician so you can see it before you roster them. Whether they suit a given list stays your decision.
How is credentialing handled?
Registration, indemnity and identity are verified when a clinician joins your bank and re-checked as they approach expiry, so a lapsed certificate surfaces before a session rather than during an audit.
StatDoctor is free for clinicians and takes no margin on the rate. Practices pay for StatHospital; pricing follows the size of your bank. No charge for an initial conversation and no obligation after one.
Which sessions do you struggle to fill?
Start with the list that goes unfilled most often and what you currently do about it. We will tell you plainly whether this is a problem we can help with.